
FDA Approves CRISPR-Based Therapeutics for Sickle Cell Disease Amid High Pricing Concerns
FDA Approves CRISPR-Based Therapeutics for Sickle Cell Disease Amid High Pricing Concerns
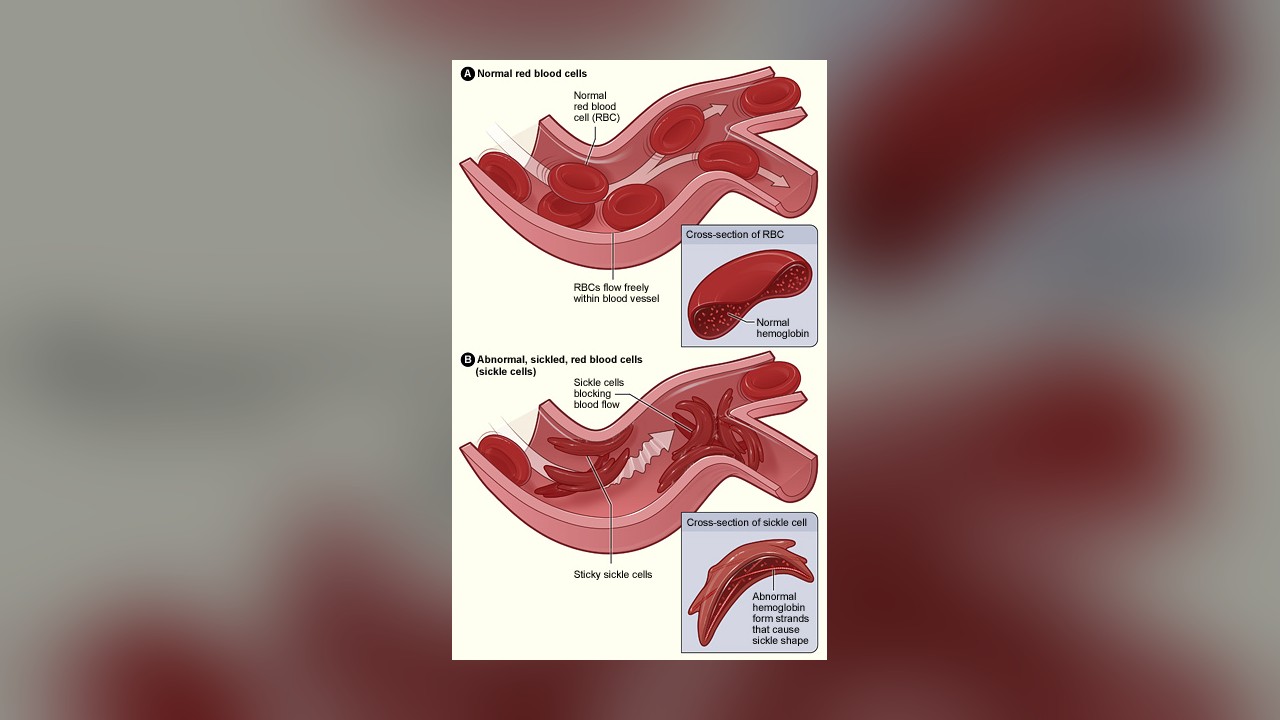
The United States Food and Drug Administration (FDA) has granted approval for the clinical deployment of two milestone gene therapies, Casgevy and Lyfgenia, designed to treat sickle cell disease (SCD) in patients aged 12 and older. The approvals represent the first commercial authorization of CRISPR-Cas9 genome editing technology within the United States healthcare system, shifting the therapeutic paradigm from symptom management to curative intervention.
Market/Global Impact
The therapeutic launch has triggered intense debate over pricing structures and access equity in the global biotechnology market. With Casgevy priced at $2.2 million and Lyfgenia at $3.1 million per patient treatment cycle, private insurers and Medicaid administrators are restructuring payment models to accommodate high upfront costs. Biotech firms Vertex Pharmaceuticals and bluebird bio saw their stock prices adjust in response to manufacturing challenges, as the cell harvesting and editing process requires specialized apheresis centers and months of laboratory modification.
Data Analysis
| Therapeutic Option | Developer | Technological Platform | Wholesale Acquisition Cost (WAC) | Clinical Trial Efficacy (Vaso-Occlusive Remission) |
|---|---|---|---|---|
| Casgevy (exagamglogene autotemcel) | Vertex Pharmaceuticals & CRISPR Therapeutics | CRISPR-Cas9 Gene Editing | $2.20 Million | 93.5% |
| Lyfgenia (lovotibeglogene autotemcel) | bluebird bio | Lentiviral Vector Delivery | $3.10 Million | 88.8% |
Note: Pricing represents initial wholesale acquisition cost and does not factor in hospitalization, conditioning regimens (busulfan), or subsequent clinical follow-up.
Forward Outlook
Securing widespread reimbursement remains the primary commercial hurdle for both therapeutics over the coming fiscal year. State-administered Medicaid programs, which cover approximately 50% of the United States sickle cell patient population, are currently evaluating value-based contract frameworks to distribute financial risk over multi-year clinical assessment windows. Additionally, the complex logistics of autologous stem cell modification will limit immediate patient throughput, prompting the development of second-generation in-vivo gene delivery mechanisms.